
Pipeline
Toward durable functional cures for persistent viral disease
At Perpetuu, we are developing AAV-delivered antibody therapies designed to address persistent viral diseases. Our pipeline focuses on durable therapeutic approaches that aim to move beyond lifelong treatment toward functional cures.
| Program | Disease | Antibody discovery | AAV vector engineering | Preclinical | Clinical | Status | Funding Support |
|---|---|---|---|---|---|---|---|
| CMVZ01 | Cytomegalovirus (CMV) in immuno-compromised patients | Antibody discovery through AAV vector engineering | Co-lead program | ||||
| HBVZ10 | Hepatitis B | Antibody discovery through AAV vector engineering and Preclinical | Co-lead, Preclinical PoC |  |
|||
| HDVZ35 | Hepatitis D | Antibody discovery | Discovery |
Chronic Hepatitis B
HBVZ10, one of Perpetuu’s two co-lead programs, targets chronic hepatitis B (CHB) and is designed to support a finite-treatment functional-cure strategy.
HBV persists in part because cccDNA can be maintained through intracellular replication and new rounds of infection. Standard-of-care nucleos(t)ide analogues such as entecavir potently inhibit intracellular viral replication but do not completely prevent extracellular virions from initiating new infection.
HBVZ10 is designed to provide sustained production of neutralizing anti-HBs antibodies from skeletal muscle, blocking the extracellular pathway of cccDNA replenishment.
Proof-of-conceptPublished preclinical validation of the Perpetuu platform
In humanized-liver mice with persistent HBV infection, a single administration of HBVZ10 produced sustained anti-HBs antibody titers ≥100,000 mIU/mL through study termination at 231 days.
As monotherapy, HBVZ10 reduced:
- Serum HBV DNA by 78–93%
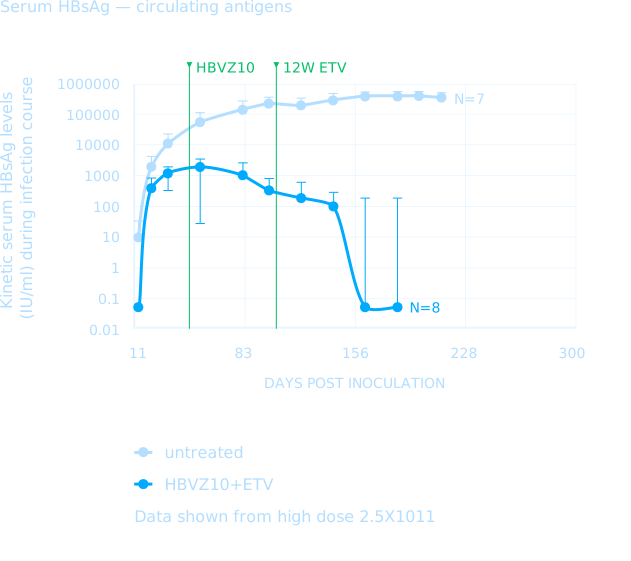
- Serum HBsAg by 80–90%
- Intrahepatic cccDNA approximately 5-fold versus control
When combined with entecavir, HBVZ10 produced:
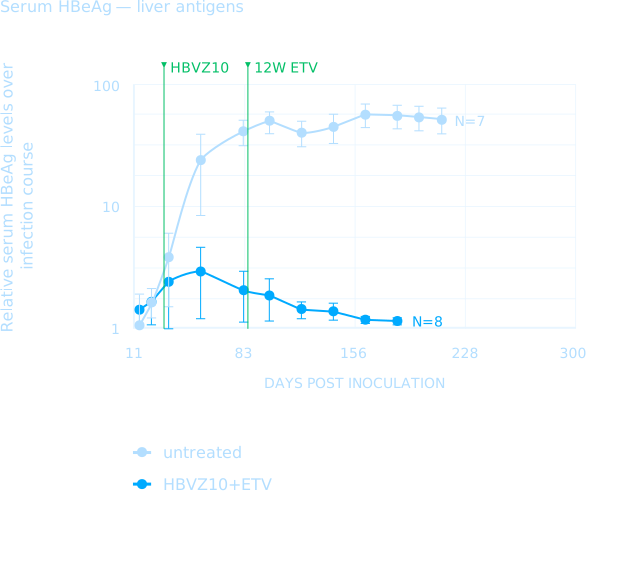
- HBsAg seroclearance in 8/9 animals (88.9%) vs. 1/10 (10%) with entecavir alone (p=0.001)
- 100-fold greater reduction in hepatic cccDNA versus entecavir alone
- 10-fold greater reduction in hepatic rcDNA versus entecavir alone
These findings support the potential of combining a durable extracellular virion blocker with an intracellular replication inhibitor as a new strategy toward functional cure.
The complete study data and supporting publications provide additional detail on the experimental design and results.
Zhang, B.H. et al. Molecular Therapy – Methods & Clinical Development 33 (2025): 4.
Infection Rebound after SOC Withdrawal
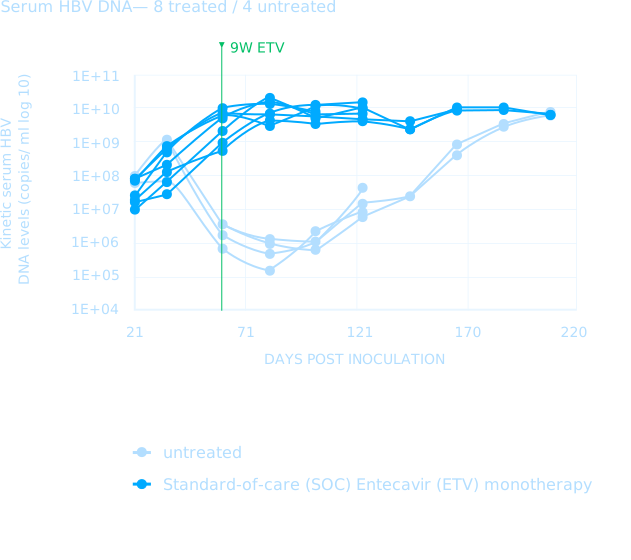
HBVZ10 + Entecavir = Durable Suppression after SOC Withdrawal
CMVZ01: Co-lead program for transplant prophylaxis
A potential single-administration approach to durable CMV protection in high-risk transplant patients
CMVZ01 is being developed to provide sustained neutralizing antibody protection during periods of highest CMV risk following transplantation. The program offers concentrated high-risk patient populations, clinically meaningful endpoints, and an opportunity to validate Perpetuu’s antibody-expression platform in a focused clinical setting.
Current standard-of-care has important limitations.
High-risk populations:
- Allogeneic stem cell transplant
- Lung transplant
- Solid organ transplant
Despite prophylaxis…
- CMV reactivation remains common
- Breakthrough infections occur
- Daily dosing required
- Significant drug-drug interactions
- Resistance reported
CMV reactivation is driven by lifelong viral latency
Latent CMV
Immunosuppression
Reactivation
CMV Disease
Hospitalization
Graft Injury
Mortality
Perpetuu approach
Single administration
Skeletal muscle produces anti-CMV antibody
Sustained neutralizing antibody exposure
Designed to provide durable protection during the highest-risk period for CMV reactivation
Donor bone marrow transplants
- CMV reactivation occurs in 50–70% of seropositive recipients
- CMV drives 10–15% mortality with SOC
- 25–40% of hospitalizations are due to CMV
- 10–15% mortality linked to CMV
Lung transplants
- 50–80% CMV infection rate
- 30–50% hospitalized due to CMV
- 10% mortality linked to CMV
Partner with us to advance the science
We are seeking strategic collaborations to advance our programs and expand application of our platform to additional chronic viral diseases.